

Charcot foot disease is a serious condition that can affect the bones, joints, and soft tissue of the foot and ankle, most often in people with diabetes who have peripheral neuropathy. Because the affected foot may not feel much pain, early damage can be easy to miss until swelling, warmth, and instability become more …


Charcot foot disease is a serious condition that can affect the bones, joints, and soft tissue of the foot and ankle, most often in people with diabetes who have peripheral neuropathy. Because the affected foot may not feel much pain, early damage can be easy to miss until swelling, warmth, and instability become more obvious.
For many diabetic patients, that delayed recognition is what makes this problem so dangerous. Charcot neuroarthropathy can progress through several stages and may end in foot collapse, significant foot deformity, skin breakdown, foot ulcers, bone infection, and even amputation if treatment does not begin early.
The good news is that early diagnosis, prompt offloading, and close follow-up can often limit joint damage and help preserve a stable, plantigrade foot meaning the sole can rest flat on the ground for safer walking. In this article, you will learn what charcot foot disease is, who is at risk, the early symptoms to watch for, and when it is time to see a foot doctor.
What Is Charcot Foot Disease?
Charcot foot disease, also called charcot foot, charcot arthropathy, charcot neuroarthropathy, or charcot neuropathic osteoarthropathy, is a destructive condition in which weakened bones and unstable foot and ankle joints begin to break down over time. It usually develops in a foot that has lost protective sensation from nerve damage.
In simple terms, the foot can keep taking stress even after a small injury because the person does not fully feel pain or sense injury the way they normally would. That can allow repeated loading, bone breakdown, and progressive joint damage across the midfoot, hindfoot, ankle joints, or other areas of the foot and ankle.
Charcot foot pathophysiology is complex, but the disease develops through a combination of loss of sensation, increased blood flow, rapid resorption of bone minerals, and an exaggerated inflammatory response. As the condition progresses, the foot’s structure becomes less stable, which raises the risk of serious foot problems.
Why Does It Happen In People With Diabetes?
Charcot foot is most commonly seen in people with diabetes-related neuropathy. Peripheral neuropathy must be present for charcot foot to develop, and diabetes mellitus is the most common cause of that neuropathy.
When diabetic neuropathy reduces protective sensation, a person may not notice minor trauma, a small fracture, or repeated stress to an injured foot. That makes it easier for acute charcot foot to start after an event that may seem small, or after no clear obvious injury at all.
High blood sugar also matters. Poor diabetes care and poor glycemic control are linked with diabetic foot problems, and strict blood sugar control is considered a key part of reducing the risk of Charcot foot in people at risk.
Other Risk Factors To Know
Diabetic neuropathy is the primary risk factor, but it is not the only one. People who have had diabetes for more than seven years, those with excess weight, and those with longstanding loss of sensation are at increased risk of developing charcot foot disease.
Other conditions that can cause neuropathy, including chronic alcoholism, spinal cord injury, and leprosy, have also been associated with charcot arthropathy. Still, diabetic charcot remains the most common scenario seen in practice.
A history of diabetic foot problems, prior ulcers, abnormal pressure points, poor footwear, and limited foot care also raise concern. When someone already has nerve damage and reduced protective sensation, even a small increase in stress across the foot increases the chance of instability.
Early Symptoms That Should Not Be Ignored
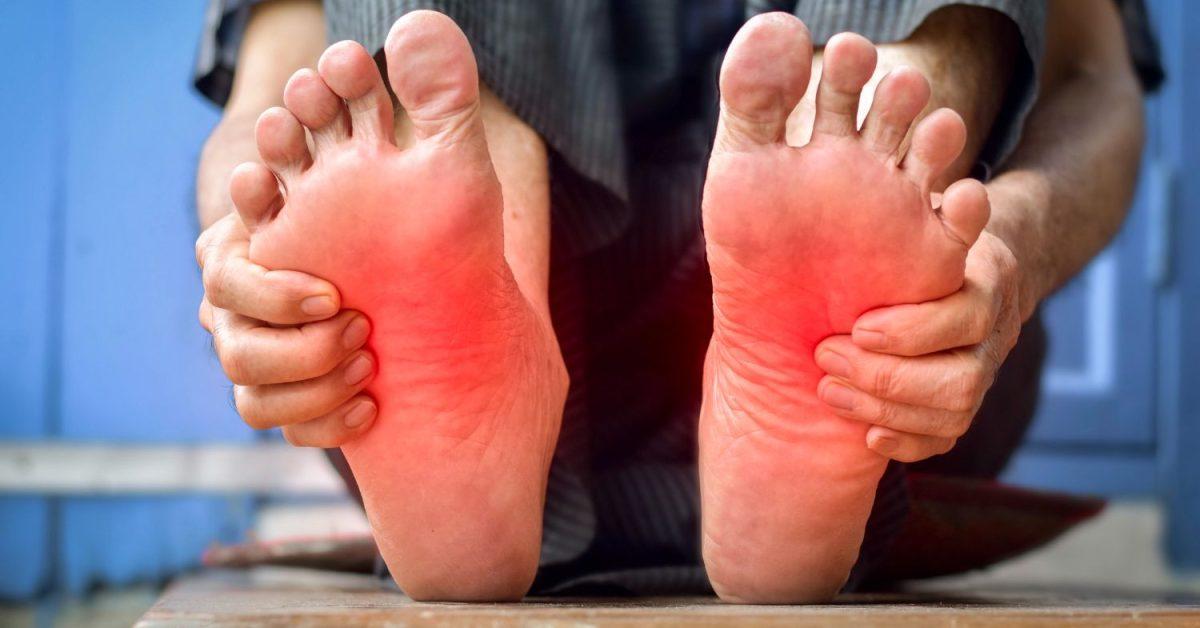
Early charcot foot often begins with swelling that occurs without an obvious injury. Many patients assume swelling means a sprain, a simple flare-up, or a minor foot problem that will settle down on its own.
Early symptoms also include redness, soft tissue swelling, and warmth. The foot may look red and inflamed, feel warmer than the other foot, and appear puffy around the midfoot, ankle, or both.
A common pattern is one swollen, warm affected foot in a person with diabetic neuropathy who does not have much pain. That relative lack of pain is one reason early diagnosis gets missed, especially in the early stages when the bones and joints are already being damaged.
Patients with diabetes should be educated to watch for unexplained warmth, redness, or swelling, even if they can still walk and do not feel pain. Early recognition of these changes is vital for preventing serious foot problems.
Why Charcot Foot May Not Hurt Much
One of the most misleading parts of charcot foot disease is that the damage can be severe even when discomfort is limited. Because nerve damage blunts normal pain signals, the person may not feel pain in proportion to the amount of injury happening inside the foot.
That is why a warm, swollen diabetic foot should never be brushed off just because it is not very painful. A person may continue walking on the foot, which can worsen instability and push the condition from early charcot foot toward more advanced stages.
How The Foot Shape Can Change Over Time
As charcot foot disease advances, progressive bone breakdown and joint instability can cause foot deformity and collapse of the foot architecture. The arch may flatten, the foot may widen, and the inside of the foot may start to turn upward.
Some patients go on to develop a rocker bottom foot, which means the midfoot collapses and creates bony prominences on the bottom of the foot. Those new pressure points can rub against shoes and increase the risk of skin breakdown.
Once there is significant deformity, the chance of chronic ulceration rises. Friction between a misshapen foot and a standard shoe can lead to blisters, pressure sores, and foot ulcers that may progress into deep infection or osteomyelitis.
Why Fast Treatment Matters
Ignoring the warning signs can lead to disability, ulceration, recurrent infection, and possible amputation. Delayed or missed diagnosis is one of the biggest reasons charcot foot becomes much harder to manage.
Ulcers are especially important. Research shows that ulceration drives much of the amputation risk in charcot arthropathy, and Charcot patients with ulcers have substantially worse limb outcomes than Charcot patients without ulcers.
Severe complications may also include chronic wounds, bone infection, deep infection, or even sepsis if the problem is not controlled promptly. Preventing these outcomes depends on early recognition, early diagnosis, and quick protection of the affected foot.
Charcot Foot Or Something Else?
A warm, swollen foot in a diabetic patient can look like several other conditions, including infection, gout, deep vein thrombosis, fracture, or sprain. Because these conditions require very different treatments, professional evaluation is essential to avoid misdiagnosis and ensure proper care.
How A Foot Doctor Diagnoses It
Diagnosis starts with the story and the exam. A foot doctor will review your medical history, ask about diabetes care, prior foot problems, recent swelling, minor trauma, and whether the other foot has had previous issues.
The physical exam focuses on swelling, temperature, redness, deformity, instability, pulses, skin condition, and whether there are wounds or abnormal pressure areas. Your doctor may also check protective sensation to see how much nerve function has been lost.
Because several conditions can look similar, your doctor also has to think about infection, gout, deep vein thrombosis, fracture, or whether an injury represents a sprained ankle vs a broken ankle, or other diabetic foot problems. That is one reason a warm, swollen foot should be evaluated promptly instead of treated as a guess.
Imaging And Testing
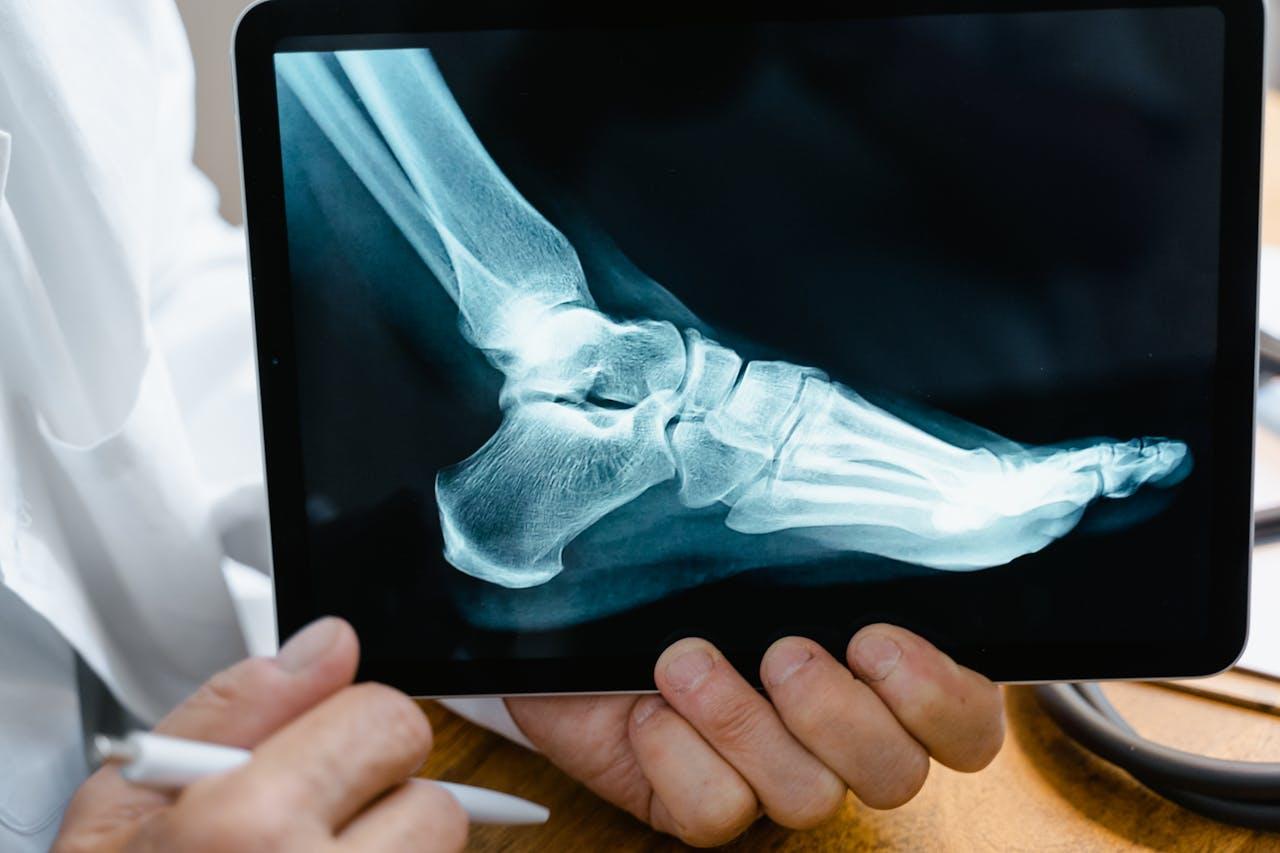
X-rays are usually the first imaging step, but early charcot foot may not always show dramatic findings at the beginning. In some cases, MRI, CT, or bone scans are used when the diagnosis is uncertain or when a doctor needs to look more closely for fractures, marrow edema, or bone infection.
Imaging helps show whether the foot and ankle joints are becoming unstable, whether there is bone fragmentation, and whether there are changes in areas such as the midfoot, hindfoot, calcaneocuboid joints, or ankle.
Testing is only part of the picture, though. A careful physical exam and clinical suspicion still matter, because early symptoms in the acute phase can appear before obvious collapse is seen on standard films.
Initial Treatment In The Acute Phase
The first priority in acute charcot foot is to protect the foot and ankle from further damage. Early recognition and prompt immobilization are central to treating charcot foot because they help prevent further deformity while the bones begin healing in a more stable position.
A total contact cast is a common initial treatment. Casting offloads the foot, reduces abnormal pressure, supports unstable structures, and aims to protect the bones and joints during the acute phase.
This stage often requires patience. Published reviews commonly describe several months of immobilization, with many patients needing roughly 3 to 6 months of offloading before the active inflammatory process settles down enough for the next phase of care.
Your doctor may also recommend a removable boot, brace, or a Charcot restraint orthotic walker in some situations, but the main goal stays the same: protect the affected foot early enough to prevent foot collapse and a more permanent foot deformity, sometimes including surgical foot and ankle procedures if conservative care is not enough.
What Happens After The Acute Phase
Once swelling and warmth improve, treatment usually shifts toward gradual return to activity and long-term protection. This often includes custom bracing, protective footwear, shoe inserts, and regular monitoring so the foot remains stable.
The overall treatment goal is not just to make the foot look better on imaging. It is to create an ulcer-free, stable, plantigrade foot meaning the sole rests flat on the ground for safer walking that can walk safely in a commercially available diabetic shoe or other appropriate protective footwear.
Lifelong protective measures are usually required after initial treatment because long-term complications can include recurrent Charcot activity in the same foot or the other foot, especially when offloading is poor or metabolic control remains suboptimal.
When Surgery May Be Needed
Not every case needs surgery, but some do. Surgery may be considered when casting, bracing, and custom footwear cannot achieve a stable, plantigrade foot, or when there is severe deformity, recurrent ulceration, instability, or prominent bone that keeps breaking down skin.
Surgical treatment aims to restore alignment, reduce abnormal pressure, and lower the chance of recurrent ulceration. In advanced cases, procedures may address joint instability, severe charcot foot deformity, or deformities involving the midfoot or ankle joints, and some patients with advanced ankle arthritis may be candidates for ankle replacement surgery.
Because Charcot foot can change the structure of the foot quickly, early evaluation by a foot and ankle specialist can help protect the foot before collapse or ulceration develops.
Preventing Ulcers And Skin Breakdown
One of the biggest concerns in charcot foot disease is skin breakdown over bony prominences. Once pressure points form on the bottom or side of the foot, even well-meaning daily activity can create friction that leads to ulcers.
That is why footwear matters so much. Strong, supportive, full-coverage shoes and other protective footwear help reduce pressure, limit rubbing, and protect an insensate diabetic foot from minor trauma.
For some patients, custom orthotics, braces, or diabetic shoes are necessary to support the foot and ankle and lower the risk of new wounds. Taking shoe fit seriously is important, especially if your foot shape has changed.
Prevention Starts With Daily Foot Care
The best treatment for diabetic foot problems is prevention. For people with diabetes, that means good blood sugar control, careful daily foot inspection, and prompt attention to any redness, swelling, blister, crack, or sore.
Daily foot inspection is especially important because patients with neuropathy may not notice an early injury. Looking at the top, bottom, heel, and between the toes can help catch changes before they turn into serious complications.
Patients at risk should also have regular follow-up with a healthcare provider. Guidance from the American Diabetes Association supports routine foot assessment, and patient education is a key part of preventing serious foot problems, including recognizing when to worry about a sprained ankle that may actually represent a more serious injury.
If you already have diabetic neuropathy, pay extra attention to unexplained warmth, swelling, or a red, inflamed-looking foot. Those early warning signs deserve a real evaluation, even when the foot does not feel badly injured.
When To See A Foot Doctor Right Away
You should contact a foot doctor quickly if one foot suddenly becomes swollen, warm, red, or visibly different from the other foot, especially if you have diabetes, peripheral neuropathy, or a history of diabetic foot problems.
Urgent evaluation is also important if you notice a new wound, drainage, foul odor, increasing deformity, trouble fitting into shoes, or any concern for infection. Those signs can point to serious complications that should not wait.
How Wisconsin Foot & Ankle Clinic Can Help
Wisconsin Foot & Ankle Clinic in Brookfield provides comprehensive foot and ankle care tailored to every stage of charcot foot disease. The clinic helps by:
-
Recognizing suspicious warm, swollen feet early through expert evaluation.
-
Confirming diagnosis with thorough exams and appropriate imaging.
-
Protecting the foot using conservative treatments like casting and offloading to prevent further damage.
-
Monitoring healing progress closely to guide safe return to activity.
-
Considering reconstructive surgery only when necessary to restore stability and prevent ulcers.
Dr. Donald T. McDonald, a fellowship-trained foot and ankle surgeon, leads the care team with advanced expertise in reconstruction and complex foot and ankle conditions. This specialized approach supports patients through every stage of charcot foot disease, helping to protect foot structure, preserve mobility, and reduce the risk of ulcers and deformity.
For patients dealing with charcot foot disease, early and specialized evaluation can make a critical difference in long-term stability, mobility, and ulcer prevention.
Conclusion
Charcot foot disease is not just another cause of swelling. It is a limb-threatening condition that can progress rapidly from early signs to significant deformity, especially when diabetic neuropathy masks the warning signals.
This article is for educational purposes and does not replace a medical evaluation. If you are experiencing unexplained swelling, redness, warmth, or shape changes in the foot or ankle in the Brookfield area, schedule a visit with Wisconsin Foot & Ankle Clinic for a clear diagnosis and a treatment plan that helps you move more safely and comfortably again.


